Full Text (PDF)
Physiotherapy and Occupational Therapy Journal 19(3):p 185-190, July - Sep 2026. | DOI: https://doi.org/10.21088/potj.0974.5777.19326.3
Original Article
A Comparative Study on the Efficacy of Low-Level Laser Therapy Versus Electrical Stimulation Along with Mime Therapy in the Rehabilitation of Acute Bell’s Palsy
K. Saraswathi, S. Ramachandran, Selvaraj Sudhakar, Koushik Kumar Nandhagopal
Author Information
Licence:
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)This license
enables reusers to distribute, remix, adapt, and build upon the material in any
medium or format for noncommercial purposes only, and only so long as
attribution is given to the creator.
Physiotherapy and Occupational Therapy Journal 19(3):p 185-190, July - Sep 2026. | DOI: https://doi.org/10.21088/potj.0974.5777.19326.3
How Cite This Article:
K. Saraswathi, S. Ramachandran, Selvaraj Sudhakar, et al. A Comparative Study on the Efficacy of Low-Level Laser Therapy Versus Electrical Stimulation Along with Mime Therapy in the Rehabilitation of Acute Bell’s Palsy. Therapy Jr. 2026; 19(3): 185-190.Timeline
Received : May 09, 2026
Accepted : June 12, 2026
Published : September 30, 2026
Abstract
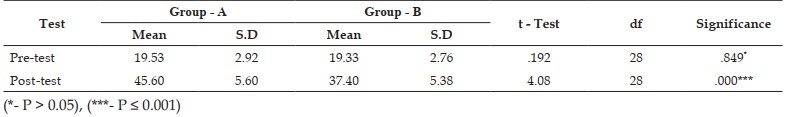
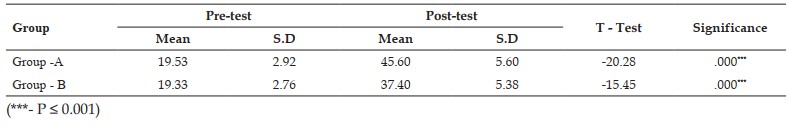
Background: Palsy of the peripheral facial nerve, unilateral, acute, idiopathic, and peripheral, is the case with Bell lectures leads to facial asymmetry and weakness. Even though a significant percentage of patients will recover on their own,partial recovery is still very frequent, especially in the more extreme cases. Low-level laser physiotherapy rehabilitation can be done using therapy (LLLT) and electrical stimulation (ES), although.comparative evidence on their effectiveness in combination with mime therapy, remains limited.1-3 Purpose: To compare the therapeutic benefit of LLLT and mime therapy and ES and mime. patients with acute Bell’s palsy therapy with the Facial Disability Index (FDI) was used to measure the situation before and after the therapy as primary outcome measure. Methods: This was a prospective, randomized, comparative study involving 30 participants who were aged 18-40 years with acute unilateral Bell’s palsy. The random sequence was produced with the help of a computer-based random number method, using an independent researcher, and was allocated.hided in sequentially numbered, opaque, sealed envelopes that were opened after baseline assessment. A blinded assessor performed the outcome assessment. Participants were randomly allotted to two equal groups (n = 15 each). LLLT was administered to Group A (795 nm, 4)J/cm2 of eight points of the facial nerve (plus mime therapy) and Group B galvanic ES (3 30 ms pulse duration at 11 motor points) and mime therapy. Both groups received three times weekly during 6 weeks and a total of 18 sessions. FDI scores were captured at the baseline and upon the intervention being completed. Result: Findings revealed a significant increase in the FDI scores of both groups following treatment (p ≤<|human|>Results: The results showed that both groups experienced significant improvement in FDI scores following treatment (p ≤ 0.001). The mean score of post intervention FDI in Group A (45.60 ± 5.60) is higher than that of Group B (37.40 ± 5.38) and the difference between groups was significant (t =4.08, df = 28, p ≤ 0.001). Conclusion: In this sample, LLLT, in combination with mime therapy was linked to increased temporary enhancement of facial functioning as compared to ES with mime therapy. These results indicate that LLLT can be an effective complement in physiotherapy rehabilitation in patients with acute Bell’s palsy, but larger studies with more years of follow-up are required to establish the result.
References
- 1. Baugh R.F., Basura G.J., Ishii L.E., Schwartz S.R., Drumheller C.M., Burkholder R., et al. Clinical practice guideline: Bell’s palsy. Otolaryngol Head Neck Surg. 2013; 149(3 Suppl): S1-S27. doi:10.1177/0194599813505967 https://doi.org/10.1177/0194599813505967
- 2. Peitersen E. Bell’s palsy: the spontaneous course of 2,500 peripheral facial nerve palsies of different etiologies. Acta Otolaryngol Suppl. 2002;(549):4-30. doi:10.1080/000164802760370736 https://doi. org/10.1080/000164802760370736
- 3. Tiemstra J.D., Khatkhate N. Bell’s palsy: diagnosis and management. Am Fam Physician. 2007; 76(7): 997-1002. h t t p s : / / w w w . a a f p . o r g / p u b s / a f p / issues/2007/1001/p997.html
- 4. Rowlands S., Hooper R., Hughes R., Burney P. The epidemiology and treatment of Bell’s palsy in the UK. Eur J Neurol. 2002; 9(1): 63-67. doi:10.1046/j.1468-1331.2002.00343.https:// doi.org/10.1046/j.1468-1331.2002.00343.x
- 5. Peitersen E. The natural history of Bell’s palsy. Am J Otol. 1982; 4(2): 107-111. https://pubmed.ncbi.nlm.nih.gov/7148998/
- 6. Murakami S., Mizobuchi M., Nakashiro Y., Doi T., Hato N., Yanagihara N. Bell palsy and herpes simplex virus: identification of viral DNA in endoneurial fluid and muscle. Ann Intern Med. 1996; 124 (1 Pt 1): 27-30. doi:10.7326/0003- 4 8 1 9 - 1 2 4 - 1 _ P a r t _ 1 - 1 9 9 6 0 1 0 1 0 - 0 0 0 0 5 https://doi.org/10.7326/0003-4819-124-1_ Part_1-199601010-00005
- 7. Holland N.J., Weiner G.M. Recent developments in Bell’s palsy. BMJ. 2004; 329(7465): 553-557. doi:10.1136/bmj.329.7465.553 https://doi.org/10.1136/bmj.329.7465.553
- 8. Gilden D.H. Clinical practice. Bell’s palsy. N Engl J Med. 2004; 351(13): 1323- 1331. doi:10.1056/NEJMcp041120 https://doi.org/10.1056/NEJMcp041120
- 9. VanSwearingen J.M., Brach J.S. Changes in facial movement and synkinesis with facial neuromuscular reeducation. Plast Reconstr Surg. 2003; 111(7): 2370-2375. doi:10.1097/01.PRS.0000060102.37413.1F h t t p s : / / d o i . o r g / 1 0 . 1 0 9 7 / 0 1 . PRS.0000060102.37413.1F
- 10. Teixeira L.J., Valbuza J.S., Prado GF. Physical therapy for Bell’s palsy (idiopathic facial paralysis). Cochrane Database Syst Rev. 2011; (12): CD006283. doi:10.1002/14651858.CD006283.pub3 https://doi.org/10.1002/14651858.CD006283. pub3
- 11. Avci P., Gupta A., Sadasivam M., Vecchio D., Pam Z., Pam N., et al. Low-level laser (light) therapy (LLLT) in skin: stimulating, healing, restoring. Semin Cutan Med Surg. 2013; 32(1): 41-52. doi:10.12788/j.sder.0003 https://doi.org/10.12788/j.sder.0003
- 12. Fargher K.A., Coulson S.E. Effectiveness of electrical stimulation for rehabilitation of facial nerve paralysis. Phys Ther Rev. 2017; 22 (3-4): 169-176. doi:10.1080/10833196.2017.1368967 https://doi.org/10.1080/10833196.2017.13689 67
- 13. Beurskens C.H.G., Heymans P.G. Mime therapy improves facial symmetry in people with long-term facial nerve paresis: a randomised controlled trial. Aust J Physiother. 2006; 52(3): 177-183. doi:10.1016/S0004- 9514(06)70026-5 https://doi.org/10.1016/ S0004-9514(06)70026-5
- 14. Javath J.M., D’Souza A.F, Rebello SR. Low level laser therapy versus electrical stimulation for the management of acute Bell’s palsy: a randomized clinical trial. Phys Treat Spec Phys Ther J. 2021; 11(4): 261-268. doi:10.32598/ptj.11.4.508.1 https://doi.org/10.32598/ptj.11.4.508.1
- 15. Ordahan B., Karahan A.Y. Role of low-level laser therapy added to facial expression exercises in patients with idiopathic facial (Bell’s) palsy. Lasers Med Sci. 2017; 32(4): 931-936. doi:10.1007/s10103-017-2188-y https://doi.org/10.1007/s10103-017-2188-y
- 16. Holland N.J. Bell’s palsy. BMJ Clin Evid. 2008;2008:1204. https://www.ncbi.nlm.nih.gov/pmc/ articles/PMC2907944/
- 17. Fargher K.A., Coulson S.E. Effectiveness of electrical stimulation for rehabilitation of facial nerve paralysis. Phys Ther Rev. 2017; 22(3-4): 169-176. doi:10.1080/10833196.2017.1368967 https://doi.org/10.1080/10833196.2017.13689 67
- 18. D’Souza A.F., Rebello S.R. Comparing the effectiveness of mime therapy and neuromuscular re-education in improving facial symmetry and function in acute Bell’s palsy: a pilot randomized clinical trial. Int J Ther Rehabil. 2021; 28(5): 1-10. doi:10.12968/ijtr.2020.0133 https://doi.org/10.12968/ijtr.2020.0133
Data Sharing Statement
There are no additional data available. All raw data and code are available upon request.
Funding
This research received no funding.
Author Contributions
All authors contributed significantly to the work and approve its publication.
Ethics Declaration
Ethical approval was obtained from the Institutional Ethical Committee of Dr. M.G.R. Educational and Research Institute, Chennai. Ref No. A-89 /PHYSIO/IRB/2023-2024
Acknowledgements
We would like to express our gratitude to the patients, their families, and all those who have contributed to this study.
About this article

Cite this article
K. Saraswathi, S. Ramachandran, Selvaraj Sudhakar, et al. A Comparative Study on the Efficacy of Low-Level Laser Therapy Versus Electrical Stimulation Along with Mime Therapy in the Rehabilitation of Acute Bell’s Palsy. Therapy Jr. 2026; 19(3): 185-190.
Licence:
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)This license
enables reusers to distribute, remix, adapt, and build upon the material in any
medium or format for noncommercial purposes only, and only so long as
attribution is given to the creator.
| Received | Accepted | Published |
|---|---|---|
| May 09, 2026 | June 12, 2026 | September 30, 2026 |
DOI: https://doi.org/10.21088/potj.0974.5777.19326.3
Keywords
Bell’s palsyLow-level laser therapyElectrical stimulationMime therapyFacial Disability IndexFacial nerve palsyPhysiotherapySearch for Similar Articles
Similar Articles
- A Study to Compare the Effectiveness of Pilates vs Back Exercises in Adolescents...
- Correlation of Physical and Motor Skills with Smashing Accuracy in Badminton Pla...
- Effect of Perioral Stimulation, Vertebral Pressure, Abdominal Co-Contraction and...
- Effectiveness of FIFA 11+ Protocol on Physical Performance among Amateur Footbal...
- Association between Foot Posture Asymmetry, Dynamic Stability, and Disability in...
Article Level Metrics
Last UpdatedSunday 27 September 2026, 06:19:35 (IST)
3414
Accesses
16
614
00
Citations
NA
NA
NA
Download citation
Article Keywords
Keyword Highlighting
Highlight selected keywords in the article text.
Timeline
| Received | May 09, 2026 |
| Accepted | June 12, 2026 |
| Published | September 30, 2026 |
licence
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)
This license
enables reusers to distribute, remix, adapt, and build upon the material in any
medium or format for noncommercial purposes only, and only so long as
attribution is given to the creator.