Full Text (PDF)
Journal of ENT and Allied Sciences 8(2):p 47-50, July - December 2023. | DOI: NA
Case Report
Submucosal Globular Tongue Swelling: A Rare Presentation of Adenoid Cystic Carcinoma
Mehneet Sawhney, Prince Handa, Anmol Rattan Kath, Nishtha Batra
Author Information
Licence:
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)This license enables reusers to distribute, remix, adapt, and build upon the material in any medium or format for noncommercial purposes only, and only so long as attribution is given to the creator.
Journal of ENT and Allied Sciences 8(2):p 47-50, July - December 2023. | DOI: NA
How Cite This Article:
Prince Handa, Mehneet Sawhney, Anmol Rattan Kath et al. Submucosal Globular Tongue Swelling: A Rare Presentation of Adenoid Cystic Carcinoma. RFP J ENT Allied Sci 2023;8(2):47–50.Timeline
Received : July 12, 2023
Accepted : October 11, 2023
Published : December 25, 2023
Abstract
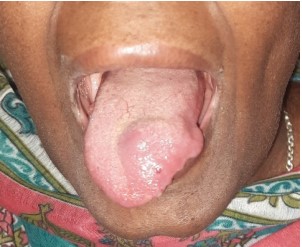
Introduction: Adenoid cystic is an infrequent malignancy of the salivary glands. Some of its unique features include slow growth, the tendency for perineural invasion, local recurrence, and the ability to metastasize. The mobile tongue's adenoid cystic carcinoma (ACC) is a rare reported case in the literature. Report: We report a rare case of adenoid cystic carcinoma, in a 55-year-old female who presented with a swelling arising in the dorsal and lateral aspect of anterior tongue to Head and Neck surgery OPD in a teritary care cancer institute in North India. Histopathology after complete excision of the mass confirmed the diagnosis of adenoid cystic carcinoma. There has been no evidence of disease following excision with tumour-free margins. Discussion: The pathophysiology of ACC is an understudied area due to the condition's rarity. Chromosomal abnormality and dysregulated MYB oncoprotein have to be thought to play a key role in the pathophysiology and proliferation of ACC. Conclusions: Adenoid cystic carcinoma of the tongueis exceedingly rare but should be considered in the differential diagnosis in patients with tongue swelling. These tumours are malignant and treatment requires surgical excision and neck dissectionfollowed by adjuvant radiotherapy.
References
- 1. Spiro RH, Huvos AG, Strong EW. Adenoid cystic carcinoma of salivary origin. A clinicopathologic study of 242 cases. Am J Surg 1974;128: 512–20.
- 2. Tang X, Zhang C, Chen R, Zhou X, Zhang Y. Treatment of adenoid cystic carcinoma of the mobile tongue with anterolateral thigh flap reconstruction. Medicine 2019;98:e15250. https://doi.org/10.1097/ md.0000000000015250.
- 3. Dillon PM, Chakraborty S, Moskaluk CA, Joshi PJ, Thomas CY. Adenoid cystic carcinoma: A review of recent advances, molecular targets, and clinical trials. Head Neck. 2016 Apr;38(4):620-7.
- 4. Luna-Ortiz K, Carmona-Luna T, Cano-Valdez AM, et al. Adenoid cystic carcinoma of the tongue–clinicopathological study and survival analysis. Head Neck Oncol 2009;1:15.
- 5. Azumi N, Battifora H. The cellular composition of adenoid cystic carcinoma. An immunohistochemical study. Cancer. 1987 Oct 01;60(7):1589-98.
- 6. Carrasco Ortiz D, Aldape Barrios B. Adenoid cystic carcinoma of the dorsum of the tongue: presentation of a case. Med Oral Patol Oral Cir Bucal 2006;11:E417–20.
- 7. Luna-Ortiz, K., Carmona-Luna, T., Cano-Valdez, A.M. et al. Adenoid cystic carcinoma of the tongue – clinicopathological study and survival analysis. Head Neck Oncol 1, 15 (2009). https://doi. org/10.1186/1758-3284-1-15.
- 8. Goldblat LI, Ellis GL: Salivary Gland Tumors of theTongue. Analysis of 55 new cases and review of literature. Cancer. 1987, 60: 74-81. 10.1002/1097-0142(19870701)60:1<74::AID-CNCR28 20600113>3.0.CO;2-B.
- 9. Tang X, Zhang C, Chen R, Zhou X, Zhang Y. Treatment of adenoid cystic carcinoma of the mobile tongue with anterolateral thigh flap reconstruction. Medicine 2019b;98:e15250. https://doi.org/10.1097/ md.0000000000015250.
- 10. Kumar, S., Agarwal, P., & Nimmi, V. (2016). Adenoid cystic carcinoma: A rare late presentation of the mobile tongue. Journal of Oral Biology and Craniofacial Research, 6(2), 164–167. doi:10.1016/j. jobcr.2016.02.001.
Data Sharing Statement
There are no additional data available. All raw data and code are available upon request.
Funding
This research received no funding.
Author Contributions
All authors contributed significantly to the work and approve its publication.
Ethics Declaration
This article does not involve any human or animal subjects, and therefore does not require ethics approval.
Acknowledgements
We would like to express our gratitude to the patients, their families, and all those who have contributed to this study.
Conflicts of Interest
No conflicts of interest in this work.
About this article

Cite this article
Prince Handa, Mehneet Sawhney, Anmol Rattan Kath et al. Submucosal Globular Tongue Swelling: A Rare Presentation of Adenoid Cystic Carcinoma. RFP J ENT Allied Sci 2023;8(2):47–50.
Licence:
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)This license enables reusers to distribute, remix, adapt, and build upon the material in any medium or format for noncommercial purposes only, and only so long as attribution is given to the creator.
| Received | Accepted | Published |
|---|---|---|
| July 12, 2023 | October 11, 2023 | December 25, 2023 |
DOI: NA
Keywords
Adenoid cystic carcinomaCarcinoma tongueOral cavityPerineural invasionLingual tumoursSearch for Similar Articles
Similar Articles
- Paediatric Subglottic Mucocele: Early Intervention and Recovery
- Managing Some Rare Parotid Masses
- Hidden Dangers of Oral Hygiene: Oropharyngeal Impalement by Toothbrush in a 3-Ye...
- Pseudomonas Aeruginosa in an Immunocompetent Individual with Acute Tonsillitis;...
- Functional Outcome of Abbe–Estlander Flap in Lower Lip Carcinoma with Commissura...
Article Level Metrics
Last UpdatedFriday 23 October 2026, 01:55:51 (IST)
1265
Accesses
6
164
00
Citations
NA
NA
NA
Download citation
Article Keywords
Keyword Highlighting
Highlight selected keywords in the article text.
Timeline
| Received | July 12, 2023 |
| Accepted | October 11, 2023 |
| Published | December 25, 2023 |
licence
Attribution-Non-commercial 4.0 International (CC BY-NC 4.0)
This license enables reusers to distribute, remix, adapt, and build upon the material in any medium or format for noncommercial purposes only, and only so long as attribution is given to the creator.